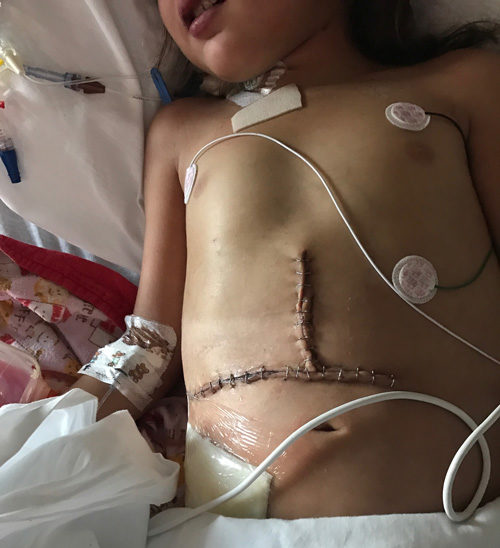
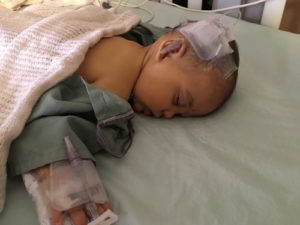
Whether you are a patient, caregiver, family member, or friend, you have a unique and important story to tell about PFIC and related diseases. PFIC family stories are one of our community’s greatest tools, as they share our strength, resilience, and the lessons we’ve learned. They also help more clearly reveal our unmet needs. This can help guide advocacy efforts and inspire scientific research to address them.
Some of our stories are about triumphs. Some are about the hardships and burdens of life with a chronic rare disease. Others may be about the support found with others on the same journey. Reading and sharing PFIC family stories can be a powerful way to empower patients and families. We encourage members of the PFIC community to share stories so that others on this journey can feel less alone. In a community that is so rare, we strive to find hope in the connections that we make with others.
Over the years, we have gathered stories from PFIC patients, families and caregivers all over the world. In addition to the stories posted below, we also have video family stories on our Youtube channel. From Sadia in Pakistan to Francesca in Italy, we all have our own story to tell about what life with PFIC looks like. Please contact us if you would like to share your PFIC story.
“He looks like a perfectly normal child, you would never know that on the inside he would be fighting for his life.”
Click below to read stories from PFIC patients & families:
The following is an excerpt from a forthcoming book called “The Best Type of New: Poems of Early Motherhood” by Germaine Thai, a PFIC mom from Malaysia:
Liver transplant. Surgery. Lifelong medication. Words that no parent would ever want to hear. Especially not when their baby was barely 3 months old, and of a tinier build than most others.
3 Months
It was a normal Sunday afternoon. We went over to my sister’s house for her housewarming, and Caleb, our son, started developing a fever. We also noticed his eyes and skin were yellow, but we didn’t think anything about the jaundice. It felt like a small problem, something that medication and a visit to the doctor would resolve. After all, jaundice in babies was quite common.
Just to be safe, we took Caleb to a private hospital emergency room. It was buzzing with chatter from patients and their families and sounds of triage from the nurses and doctors. We took our number and sat down, waiting for our turn. Caleb curiously looked around, absorbing the environment around him and observing people as they came and went. Our turn came, and a young doctor walked in, smiling at us as she said hello to Caleb. My husband started explaining our concerns and Caleb’s symptoms, as I watched the doctor’s face become increasingly concerned.
“How old is he again?”
“He just turned 3 months old.”
“When did the jaundice start?”
“A couple of days ago. We thought to just monitor in case it went away, but it didn’t. Today would be day 4 since we noticed the jaundice.”
“Ok, and the fever? When did it start?”
“Just last night, and it went away. In the afternoon the fever started again, so we brought him in.”
“Got it, we will have to take some blood samples to run tests. The fever could be an infection so we’ll get that checked.”
“Great. What about the jaundice? Would it go away after a few days? Is there any medication to take, or maybe some phototherapy?”
“Umm.. How is the colour of Caleb’s stools?”
“Oh, it’s yellow. We were told yellow is good.”
“Yes, but is it bright yellow? Or pale yellow?”
“A mixture. Sometimes it’s bright yellow, but other times it is light yellow.”
“Hmm I see. That’s actually not very normal, as the stools of a healthy baby are normally bright yellow. I will need to refer you to a gastro pediatric doctor for further consultation. Let me just check if you need to be admitted today, or if you can head home first and come back for the consultation on a different day.”
“Admitted? Isn’t it just a normal newborn symptom? Many babies have jaundice.”
“It’s normal in newborns less than a month old, but not so beyond that.”
Our hearts sank. It wasn’t normal? A referral to a specialist? Admission? We were blindsided by the doctor’s words.
Taken by surprise, we had to be admitted. We had our regular pediatric doctor and a gastroenterology pediatric doctor assigned to us. Vials and vials of blood taken, dozens of tests ran. Caleb did an ultrasound and a HIDA scan, in attempts to identify why the jaundice was happening. It was tough having a 3 month old in the hospital, with so many lines and tubes attached to him. We couldn’t walk around with him when he was fussy, or properly rock him to sleep. The hospital was a new environment which also meant lots of adjustments.
A night in, Caleb’s tests came back and his haemoglobin was very low. The hospital suggested that we admit Caleb into the Neonatal ICU (NICU). We were scared. We already had our taste of the NICU when Caleb was born prematurely. We never thought we would end up back there again. Returning to our bedroom without Caleb for the first time since he was born was tough. The room felt so empty, and we felt so lost without our usual routine of night feeds and bouncing him to sleep. I prayed that he would be all better soon, back in our arms in the comfort of our home.
After a week, our patience was wearing thin. What was the problem? Why did they run so many tests, yet still could not find the root cause of Caleb’s infection and jaundice? Anxiety and fear had found their way into our bubble of happiness. The fever had gone down after medication and a blood transfusion solved the low haemoglobin. Wasn’t it time to go home?
The gastroenterology doctor, Doctor Chu, was curt and detached. He didn’t play with Caleb, nor did he try to be positive or comforting to us – first time parents that had to go through this series of tests and weeks of hospitalization. Doctor Chu explained to us that Caleb’s bile flow was not normal. Something was blocking the bile from flowing out through his stools (hence the pale yellow colour).
He had a couple of theories that could explain the jaundice:
Theory 1
Caleb had a blocked bile duct that obstructed his bile flow.
Solution: A small incision and surgery to see exactly what the issue was internally, and flush out the obstruction in the bile duct to clear the passage for bile flow. A one time procedure that would resolve the problem
Theory 2
Caleb was born with insufficient bile ducts. The reduced number of ducts then could not allow for bile to flow normally.
Solution: No particular solution, symptomatic treatments and monitoring.
Theory 3
Caleb had a rare medical condition that affected his liver function. The initial suspicion was biliary atresia.
Solution: For biliary atresia, a major surgery called Kasai had to be done immediately. If the Kasai was done late, it would be ineffective and a liver transplant might be needed.
We were shocked and paralyzed in fear. How did it escalate from a simple case of jaundice into this? Transplant? Rare medical condition? My brain stopped working and zoned out of the later information, as Doctor Chu droned on in the background about support groups and possible treatments for biliary atresia. The medical jargon was hard to grasp, especially in the state of shock that we were in. Our brains just could not process the severity of Caleb’s symptoms.
We had to decide very soon on whether to proceed with the surgery for further confirmation of the theories above. There was no time to properly process anything. Doctor Chu was throwing a hefty number out for the surgery cost, in case of a Kasai surgery (to be done together as one surgery), pushing us for a decision. His lack of empathy left us reeling with a deep sense of negativity and fear.
An emergency family meeting was called to break the news to the grandparents of both sides. We discussed options and possibilities based on the little that we knew. I was personally a wreck, tears falling down my cheeks as my mind raced ahead thinking about Caleb’s future, imagining the scenarios that could happen. Just last week, our discussions centered around a “Happy 100 days” celebration, but we’re now planning hospital visits and surgery options.
—
The surgery day came. My husband and I waited in the family holding area. The surgeon briefed us about the procedure, assuring us that he would come out before two hours to update us on whether a Kasai was needed. I could still recall that day so clearly – waiting for a diagnosis from the surgeon made every minute of surgery feel like hours. The room was too cold, too sterile. I felt like I should be praying, or crying. At the same time, I felt like I had to be strong for Caleb. He was our little warrior going through the surgery inside, fighting to go home.
Good news! The surgeon approached us about an hour into the surgery to confirm that it was not biliary atresia. It was very likely Theory 1, where his bile ducts were blocked by something that could be flushed out. They would proceed to flush out the ducts and finish the surgery. We were elated and relieved, happy to have found the problem and a permanent solution.
We were discharged a few days later with weekly follow-ups. Caleb’s bilirubin levels, which indicated the severity of his jaundice, started coming down gradually and his blood tests seemed to be trending well. We continued with life. I went back to work after 4 months of maternity leave and all was great. The only thing we needed to catch up on was Caleb’s developmental milestones, which regressed after weeks of lying in the hospital. No big deal, we knew that he would catch up anyway. We were back in our happy bubble, worrying about the most mundane things like daycare and nap schedules.
7 Months
Post the minor surgery at 3 months, Caleb was doing great. His blood tests continued to trend well and we were expecting the bilirubin levels to normalize over time. He was catching up with his growth and we were excited to introduce him to solid foods. His developmental milestones were also trending positively. For a couple of months, everything felt normal.
We had made plans to register Caleb into a daycare when I returned to work. We adjusted into a rhythm of sending him off and picking him up every day. However, similar to any parent who experienced daycare for their little ones, Caleb started to fall sick quite frequently. Each episode of sickness meant my annual leave slowly depleted, which defeated the purpose of sending him to daycare. Caleb would be fussy, unwell and cranky. Worst of all, he would lose weight every time he fell sick. We decided we would stick it out for a few months. After all, most kids just need a little time to build up their immune systems. Meanwhile at work, I struggled to adjust. I wondered how working mums could power through constant pumping while attending meetings, getting work done and everything in between. There were constant running lists in my head – things to pack for Caleb, things to bring back home from the mother’s room, things to get done for work, things to buy for the little one. The mum brain never switched off, and my brain was in constant overdrive.
Months went by. When Caleb was around 6 months, his blood tests suddenly showed a spike in bilirubin. He started becoming jaundiced again, visibly. Immediately, we were worried. That meant the supposed fix to the problem did not work, and the root cause was still unknown. Doctor Chu had a few additional theories, as we had already ruled out the initial 3 theories during the surgery. We went down the rabbit hole of diseases that were rare. We were told that it was likely something genetic. Doctor Chu’s worried expressions during our hospital visits didn’t sit well with us. We knew it was going to be a tough uphill journey from here on, as all paths for rare diseases were.
Constant visits at the private hospital started to burn a hole in our pockets. Somewhere in the fine print of the insurance policy that we bought for Caleb, was a line that stated “all congenital diseases are not covered within the policy”. Most, if not all, genetic diseases would be considered as congenital as chromosomal abnormalities occur before birth. This broad rule applied for all insurance companies in Malaysia, as the government does not mandate a compulsory inclusion of these conditions into the policies. Unlike some other countries, the government funding to support rare genetic conditions was also very limited in Malaysia. We knew that the chances of getting any financial support in the long run would be almost impossible.
On top of that, on the expertise and experience fronts, there was only one gastro pediatric doctor in the private hospital we went to, and we desperately wanted a second opinion. There was a big “what if” lingering over us, wondering if this grave diagnosis of a rare disease was wrong. Google became our best friend, as we searched for experienced doctors that we could consult. However, we realized that unlike restaurants or dentists, there was no proper rating for doctors online. How would we know who to trust for a second opinion? How do we find the best doctor for Caleb?
We asked around with friends and family, matched them with referrals from Doctor Chu and selected a doctor from a public hospital. In Malaysia, it was a known fact that public hospitals had the best set of doctors. The cases and exposure they get from treating mass volumes of patients at public hospitals meant that they had a higher chance of treating complex and rare conditions. There was a team of experienced doctors that discussed patient cases together, and that comforted us a lot.
Professor Lim was our attending doctor. He was a ray of sunshine, one we so desperately needed. His calm and methodical approach to explaining Caleb’s condition assured us that we would figure things out, together as a team. Caleb was admitted for two weeks into the public hospital. Again, Caleb had to do dozens of tests as we went through the process of eliminating possibilities and conditions – each more rare than the last. Citrine deficiency, Alagille syndrome and Progressive Familial Intrahepatic Cholestasis (PFIC) were among the suspects causing the jaundice. Most of them were liver related genetic conditions. A liver biopsy, more ultrasounds, blood tests and even an eye test.
After a long two weeks, we had whittled it down to a possible diagnosis: PFIC, subtype 1. We knew it was a condition that was likely, but it was still so difficult to hear. A bitter pill to swallow, one that refused to go down my throat. We were referred to the genetics department, as they needed to send Caleb’s blood samples to Korea for confirmation of the diagnosis. The RM5,000 genetic test was a broad one, going through the various genetic strands to find anomalies. Malaysia did not have the capability yet to run such broad genetic testing, as genetic studies in Malaysia were quite new. By this point, we had already racked up hospital bills of RM20,000. It was an unexpected cost beyond a baby’s already expensive expenses of diapers and milk powder, but we needed to get to the bottom of his diagnosis. We needed to have some answers, once and for all, so that we knew what we were dealing with. The results would come back in a couple of months.
With this new diagnosis, we knew that Caleb would be better off at home, away from other children to avoid falling ill so often. We procured a helper and pulled him out of daycare.
10 Months
Caleb’s smiles and antics powered us through the months. A clever and cheeky boy, at 10 months old, he could now crawl around quite quickly and give giggles to things that he found amusing. His love for food continued growing as he tried different flavours. Blueberries and bananas became an obsession. “Wheels on the Bus” became our daily anthem (cue the parents who sing the same song a hundred times on repeat). He started developing stranger danger, which showed us that he was quite introverted, potentially due to the lack of exposure to other children his age.
As we waited for the results of the genetic testing, we started research on a few rare genetic diseases, particularly on PFIC. As we read about the disease, we understood that a lot was unknown at this point. PFIC is estimated to affect 1 in 50,000 or 100,000 births. Translating that to the current Malaysian population, that would mean a rough estimate of 500 Malaysians affected by this condition across all ages. Our doctors in the public hospital have only seen or heard of less than 10 cases collectively in Malaysia, across the few known subtypes of PFIC. Many genetic conditions suffer the same fate of limited information, as the world continues to develop research and understanding on the complicated field of genetics. I thought many times on whether I would prefer the outcome of naming Caleb’s root cause as PFIC, or the outcome of not getting a root cause at all. I guess it would be better to name his condition. The little information out there would be better than none at all.
The diagnosis would not change his treatment options. Caleb’s treatment was symptomatic, with the worst symptom being this unbearable constant itch, medically known as pruritus. The itch was internal, as his body had difficulties reabsorbing bile, which caused the bile salts to then recirculate in his blood stream and cause internal itch. He had to have mittens on all the time. Without them, he would scratch and rub any exposed body parts until they bled. This constant, horrible itch happened around the clock, and through the nights, sleep was not peaceful. We would wake up to crying bouts, strewn mittens and bleeding patches on his face or inside his ears. As he became more aware of the itch and how to scratch his body parts in attempts to alleviate the itch temporarily, bleeding and scabs became a normalcy in our lives.
We tried everything: lotions, creams, cold pillows, hot showers, wet towels, special scratch items and all the known medications we could get our hands on in Malaysia. Some things worked for temporary relief, others had no effect at all. There would be days of severe itch, where nothing could be done to soothe his crying and fussing, as well as his scratching of exposed body parts. On those days and long nights, even screen time barely worked to drag Caleb’s attention away from the itch. It was tiring for us, but tormenting for Caleb. His meals would be disrupted by the bouts of itch, and growth remained slow and below the national growth curve. He couldn’t play properly, nor could he get peaceful naps beyond 1 hour – not even when he was exhausted from a night of minimal sleeping. There were nights of barely any sleep for all of us, which resulted in perpetually tired parents and a very cranky baby.
And then there were days that seemed somewhat normal. Minimal itch meant great appetites and good moods, laughing and smiling through his play times. We could get about 5 to 6 hours of sleep at night, although still broken by milk feeds and times of itch in the night. We brought him to weekend enrichment classes to expose him to music, language and socializing with a few other children his age. During the good days, he really enjoyed classes and participated actively, swaying to the music and playing with the toys. We tried to figure out correlations and causations of his routine to the itch, but in the end concluded that it was cyclical and random. There was no clear trigger, and there was no clear treatment.
At this age, many other babies were doing baby-led weaning and mastering their pincer grips. For Caleb, meal times were a hit or miss occasion. The itch made it unpredictable, so we prioritized nutrition over everything else. Meals were fed as quickly as we could to ensure that he was full, then we allowed for some practice on self-feeding if his condition on the day allowed for it.
Months of limited sleep and handling Caleb’s itch started to wear us down. As parents, it was difficult to accept that we could not do much to help Caleb. Watching him suffer with the itch was very difficult. All we could do was hold him and wipe him down with a wet towel, until the severe episodes tided over. It sometimes took us hours to get over an episode, just to have the next one start an hour later. Mentally and physically, my husband and I were running on low battery. We wondered whether it would get better. I knew we would survive it somehow – we had to, there was no other choice, but at what cost?
We were very lucky to have our village of supporters. Caleb’s paternal and maternal grandparents, along with our extended families, gave us so much support and love. They helped to take care of Caleb on weekends so we could nap and run errands. This allowed us to get some much needed alone time to recharge and refuel. Our friends would plan meetups around our difficult time slots, which we really appreciated. Close friends helped us pore through social media and China-led research documents to see if there were new developments. Colleagues and our bosses gave us the space we needed and flexibility to care for Caleb. Despite the whole experience being so tough, we were so loved and very blessed. Our village kept us sane and kept us going.
The day came for us to collect the genetic test results. We were part nervous, part curious walking into the doctor’s office. It was confirmed: Caleb had PFIC subtype 1. The doctor went on to explain about the mutation of the gene and how Caleb inherited one part of a mutated, recessive gene from both of us. Again, we found ourselves caught in this new world of understanding the basics of genetic mutations, with medical jargons that kept piling up. It felt overwhelming and underwhelming at the same time to get his diagnosis confirmed. A deep sense of sadness for the lifetime medical management that Caleb probably needed because of his condition. A bit of relief that we finally made sense of the root cause of his jaundice and itch. A huge sense of fear in handling this rare genetic condition, with the little information that was known in the world today about it.
We both read up more about PFIC and it was a really scary read knowing that it was going to be our reality for Caleb’s lifetime. We were living with some of the symptoms already: the jaundice, horrible itch (pruritus), fat soluble vitamin deficiencies and growth issues. We learnt that Caleb’s liver needed close monitoring through constant blood tests to ensure that his liver functions were still good. There was a big chance that Caleb would need a liver transplant within the first decade of his life, as the bile acids that could not recirculate properly within his body would slowly build up in the liver cells. The accumulation of bile acids in the liver cells was toxic and would cause damage to these liver cells, causing the liver to slowly fail. On top of these, for PFIC type 1, there were potential hearing problems, chronic diarrhoea, chronic cough and irritation of the pancreas. Everything needed monitoring and checks.
The processing of emotions after the diagnosis was really tough. I cried in the shower, long and hard for days. I kept asking the “Whys”. Why Caleb? Why us? Why did this difficult path seem so impossible to walk? Why couldn’t he just grow up like other little boys? Why did he have to suffer so much? I was in a daze of denial for a week, tearing when I spoke about it to others, while trying to come to terms with his condition. No one truly understood how difficult it was except our immediate families, who have taken care of him personally. The condition felt isolating and incredibly lonely, as the rarity of it meant I couldn’t even speak to parents in Malaysia who had prior experiences. Acceptance and grief came in waves, tiding me under when I was alone for a few minutes. Defeat mixed with heartbreaking sadness knowing what was to come. Fear to hope for an outcome that might not be attainable.
Something changed after a few nights of shower cries. There was a determination and hope within me to push for change. A feeling that we were dealt this card to help raise awareness for this community, to try and better the lives of the little children who were also gastro patients. My husband’s finding of a new water-soluble vitamin from Europe actually opened a new door for many other patients, as this one vitamin replaced individual doses of vitamins A, D, E and K for patients. I was hopeful that there would be more findings that could help the wider community who were also struggling through similar diseases.
Through reading about PFIC, we stumbled upon the PFIC Network. The PFIC network was a global community hub for patients, caregivers and anyone who wanted to know more about PFIC. The website was easy to understand and we were amazed by the advocacy globally that was happening, specifically for this condition.
We were added to a Facebook group with hundreds of other families that had gone through the same journeys. Most of the members were from the United States, Canada and Europe. Scrolling through the photos and posts gave us so much more perspective on the disease. Everyone was really welcoming, sharing their own experiences, wins and losses. The support was incredible. There was no need to explain how horrible the itch was, or how tired we were as parents. The network knew and understood more than anyone else. It meant the world that we had a group of experienced parents to ask information from. Questions posed in the group got responses from around the world, with real experiences and advice from different hospitals worldwide.
Suddenly, the unknown nature of PFIC didn’t seem as daunting anymore. We had small villages dotted across the world, championing awareness and research for this cause. Connecting with some of the families through the network has been amazing for us to really accept Caleb’s diagnosis. We found hope in pushing through.
1 Year
Time passed, quickly and slowly at the same time. The days were long, but the months felt short. The fourth trimester that seemed so difficult at that time felt like ages ago, with the intensity of caring for a newborn dulled by time. Each day that was difficult, passed. A new day always came, and every day brought us a lot of joy and memories as a family.
Whenever possible, we wanted Caleb to grow up like any other kid. We took him out to malls, restaurants and holidays. He had swimming lessons for a couple of months, but we had to stop that as he kept falling sick. Family and friends met him and made him feel loved. Caleb picked out his own toys. Boundaries were set when he threw items. He grew up alongside our dog and we had to teach him that pulling the dog’s tail was wrong.
Caleb was turning one and we wanted to do a celebration for him. We invited 80 of our family members and friends to join us. The grandparents bought him a little Tigger outfit, as he was born in the year of the tiger. We decorated the cafe with safari-themed balloons and items, and ordered a customized cake for him. It would not be an occasion that he would remember, but it was a celebration for our little champ who smiled and laughed so much despite his condition. We wanted to make him feel special for the day.
Hospital days still continued to be a part of our regular routine. We spoke to our doctor about the treatment possibilities, especially in alleviating the pruritus for Caleb. There were many days of walking into the doctor’s office with blood dripping down his face, caused by his constant scratching or fresh wounds from a difficult night. Besides all the known medications available in Malaysia (of which we had tried them all), there were no other non-invasive options.
The next steps would be to explore surgical options, which also had levels of risk. A less severe surgery that had a decent success rate was biliary diversion; rerouting the body circuit to expel out some bile and reduce the amount of bile acid recirculation in the body. Bile acid was believed to be the main cause of his itch. This would technically solve the pruritus and delay or even prevent the liver from failing. The other option for surgery would be a liver transplant, which has been the most successful method globally of curing pruritus and improving quality of life for patients, but also has the highest risk. This option would mean lifetime immunosuppressants, after undergoing a major surgery with many possible complications. The surgical options sounded scary. We shuddered at the thought of Caleb going into the operating room yet again. At this point, we knew the options were there but we were not strongly considering them yet.
From the PFIC community, we knew that there was a new medication available. This medication was an IBAT (ileal bile acid transporter) inhibitor that works by blocking the reabsorption of bile acids in the small intestine, specifically in the ileum. Within the community, we saw parents commenting about the efficacy of these drugs for their children and it gave us a lot of hope. If the medication was effective for the child, it would be effective to stop pruritus and would work like a biliary diversion, without the surgery. There were only two such drugs in the global market, both approved in the United States by the FDA (Food and Drug Administration). However, there was no way of getting these medications into Malaysia. When we spoke to our doctors, it sounded like an almost impossible task, or at least one that would take a really long time.
These are orphan drugs currently given on a compassionate basis to patients, but both companies were aiming to commercialize these drugs in the future. When they do, the cost would be too high for us to afford, as medical insurance and the government aid both would not cover this cost. We knew that the costs were piling up. Just for check ups, medication and supplements related to Caleb’s condition, we were spending RM500 to RM1,000 a month. He also needed a special milk formula for easier absorption of fat, which costs 1.5 times higher than normal milk powders. Despite all these facts, we wanted Caleb to try this IBAT inhibitor. If it worked for him, we would figure out the cost later.
My husband was really good at all the medical terminologies and understood the research papers on PFIC a lot better than I could. Somehow, as he was reading about these orphan drugs, he stumbled upon an email for one of the pharmaceutical companies producing this IBAT inhibitor. He took a chance and emailed the contact person linked to the research paper, explaining Caleb’s condition and our inability to get the drug in Malaysia. It was a really slim chance of even getting a reply. Surprisingly, after a couple of days, we did get a reply, and a really positive one! We got redirected to conversations with the Asia team, discussing options. After a few months of discussions with both the pharmaceutical company and our doctors, we managed to obtain compassionate use of the drug via Singapore. We were ecstatic, hoping that this might be life changing for our little family.
We arranged to get the drug through Singapore, where the drug already had approvals and doctors were actively prescribing this orphan drug to other patients. This meant that we had to travel into Singapore every 3 months with Caleb. The pharmaceutical company was collecting data points to determine the success of the drug for multiple rare liver conditions. It was a difficult task to get statistically significant sample sizes, as the number of patients in these rare conditions were so small. Amongst patients with PFIC, some had already undergone surgical options or transplants so those were also not the target audience to determine the orphan drug’s success. An additional challenge was that the medication had to be transported back at refrigerated temperatures. We started off logistically arranging ice packs for the journey and ended up buying a special container used to transport insulin for easier transportation.
We were so grateful to the doctor in Singapore who accepted our case. Professor Mary wanted to help as much as she could, and when our doctor in Malaysia reached out, she gladly invited us over and made arrangements for the medication accordingly. Traveling with a baby was challenging but Singapore was great, with the efficiency of their transportation hubs and a spectrum of activities for toddlers to explore. We were excited to start this medication – anything at all that could help little Caleb live a life of better quality. At this point, his poor sleep quality and relentless itch had caused both his physical growth and his development to be severely behind his age milestones. I could not even begin to imagine the feeling of continuous itch that could not be scratched away. Caleb’s strength and ability to even function somewhat normally amazed me.
Officially, we started Caleb on the orphan drug when he was 1.5 years old. We knew that it would take a couple of weeks or even months before it showed any results, with a commitment that we would try it out for 6 months before reaching any conclusions. A few weeks in, we saw slight improvements to his pruritus but it wasn’t significant enough for him to stop scratching. He was experiencing less episodes of intense itch, though still covered in wounds and scabs from bleeding scars. Praying for a miracle, we continued on with the Singapore commutes, Malaysia checkups and this orphan drug.
It was rewarding to see Caleb take his first steps. He was at an age where a vehicle was almost always in his hand, obsessed with all objects with wheels. Trains and construction vehicles were newfound loves. We took him out to petting zoos and cafes, as well as play dates with friend groups. We often got questions about his scars and wounds, but it was quite difficult for us to articulate his condition in a few short sentences. My husband and I caught up on sleep when possible on weekends, as we were both working parents. We had to be selective on meetups with friends and I did not have the time and energy to really kickstart my fitness routine postpartum. I was grateful to have a great support system, which enabled me to go for some work travels and a few promotional activities for my first book. All in all, it was a tough year trying to juggle everything at the same time.
Month 5 of the orphan drug usage came about and it was still the same. Minimal efficacy, still bad pruritus for Caleb. At this point, we knew that this orphan drug unfortunately did not work for Caleb. It was not going to be our salvation. It was time to consider surgical options if we ever wanted to improve his quality of life.
We debated long and hard as parents on what the right move was.Would we keep things status quo until his liver really failed, or try the biliary diversion? Would it be right to put Caleb under the knife for a chance at a better life? How long would we be able to live with the pruritus, and how long should Caleb suffer like this before we explored surgical options? There were no right answers. We voiced this debate to Professor Lim and he gently advised us to wait for the outcome of a multidisciplinary team meeting that he would set up to discuss options for Caleb. The meeting would include surgeons, the Malaysian team of doctors and our Singapore doctor. Professor Lim would also reach out to contacts in the United Kingdom to get their thoughts, as they had more experience dealing with PFIC.
2 Years
We were moving ahead with the biliary diversion, which was the recommendation of the multidisciplinary meeting. Weeks of deliberation within our family and with the doctors firmed up our decision. Now that we had decided to proceed with the surgery, we still had to decide on the type of surgery, as there were various types of biliary diversions. Would we do an internal diversion or an external one? An external diversion would mean a stoma bag for life, but it had better known success rates over the years. Internal diversions were a newer solution which did not have as many success stories yet. We felt that an internal diversion was a better option for quality of life as a stoma bag would be very difficult to manage for a toddler.
While researching the different types of internal diversions, my husband stumbled upon a research paper detailing a new method from this hospital in Beijing. The paper specifically quoted that this method was successful for PFIC type 1 patients, with a reasonably significant sample size over the past decade. It sounded like a dream: finding this solution specifically tailored for Caleb’s rare condition, with long term results that were promising, including the key result of patients avoiding a liver transplant with this surgery. We were sold.
Questions on whether this hospital was reputable came about. We had relatives in Beijing so we asked around, and all checks came back positive. The hospital was one of the bigger pediatric public hospitals around. We floated the idea of doing this type of surgery in Malaysia to our team of doctors, but the type of surgery that was recommended here was the more conventional way of internal diversion. Torn on what to do, on a whim, we shot an email to the Beijing hospital. There was a doctor’s email that was listed on the research paper so we tried our luck. I assumed that the cost of doing the operation there would be exorbitant for foreigners anyway, but we had nothing to lose.
Two days later, we got a reply from Professor Mei, the doctor from the Beijing hospital. She was very detailed in her explanations and reviewed Caleb’s case thoroughly. Professor Mei welcomed us to Beijing to do the surgery there, and surprisingly, the cost of performing the surgery in China was only slightly more expensive than doing the surgery in Malaysia. Finding that this was an actual possibility, we debated long and hard about the pros and cons of Beijing. We wouldn’t have our village in Beijing, language was going to be challenging and follow-up communications might be difficult as this hospital did not have a working relationship with our current Malaysian hospital. The pros outweighed the cons though, as they had a lot of experience with internal diversions (Malaysia has never done an internal diversion before) and we could live with my uncle who was based in Beijing.
We decided to go for it. We had to do what we thought would give Caleb the best fighting chance.The 2 months leading up to the journey was hectic. Flights were booked, plans were made. We had to communicate with both Beijing and Malaysia doctors to make sure arrangements were in place. Our Mandarin levels were elementary, so we knew that translating medical terms in Mandarin was going to be a challenge. Only Professor Mei and one other doctor could speak English, which meant most of the staff would likely be conversing to us in Mandarin. We were supposed to go over for 2 to 3 weeks, with the surgery and his recovery time factored in. Packing for a few days of vacation was already tough; packing for weeks at once was a whole new ball game. China had their own apps: payments, ride-hailing, food delivery, communications, maps. Everything had to be downloaded beforehand and ready for our travels.
The day of our flight came quickly and it was the week of Christmas. It ended up being one of the most difficult flights we had ever had with Caleb. He was cranky due to lack of sleep going into this midnight flight and extremely itchy. During the flight, he kept scratching and rubbing his face, which then resulted in bleeding from a wound on his face. We had to press down on the wound to stop the bleeding, but when we did, he screamed. Surrounding passengers were staring at us; annoyance from the screaming baby and curiosity in what was happening. We had a pile of bloody tissues on the tray table and an inconsolable toddler. This went on for hours.
Beijing was in the middle of its winter season, which meant we had to prepare layers of clothes for our trip. The weather was windy and dry, fluctuating between 0 to 5 degrees on most days. We were grateful that my uncle had a car and drove us around. The next day, we went with my aunt to check in at the hospital. We were shocked at the sheer amount of people walking around the hospital lobby – easily triple the volume of patients we had back in Malaysia. It was overwhelming as people were pushing forward on their way, and we had no idea where to start or how to register.
Somehow, we managed to get everything sorted and found our way to the children’s ward. There was no bed available in the rooms, so we were given a bed in the corridor together with a small stool. How were we supposed to sleep in the corridor? The bed was only large enough for Caleb, which meant that I had to somehow fall asleep on the stool. I peeked into the rooms: 6-bedders with a shared bathroom, with only one parent permitted for each child. This again shocked me, as the size of the room would typically be a twin room back in Malaysia.
The surgery took place two days after we checked in at the hospital. Professor Mei explained the procedure to us and mentioned it would take two hours. On the day of the surgery, we carried Caleb to the operating theatre before handing him off to a nurse. There was nothing else we could do except wait and pray. It was exactly like the movies, where they had a room for all the parents to wait and a large TV screen showing the status of all the surgeries. The atmosphere in the room was charged with emotion. Many parents had tears down their cheeks, others clung onto each other. We had to be strong – our little warriors were fighting fiercely inside the operating rooms.
Two hours later, Professor Mei came out and told us that the surgery went well. We were so relieved. Caleb would go straight into the ICU for observation and transfer out to the wards after a few days. We wheeled him down to the ICU, but we could not visit him while he was in the ICU. The only form of communication was a WeChat group with reports twice a day of whether Caleb had eaten, pooped or had any fever. Beyond that, we couldn’t even get pictures or videos of him as the nurses in this public hospital did not have bandwidth. It was even more challenging as we could not get a proper hold of the doctors. Professor Mei had multiple surgeries throughout the day and she had to do clinics and ward rounds, which meant replies to our messages only came in early in the morning or late at night. We were worried and there was no means to get updates on Caleb’s condition, which made the worrying a lot worse.
A few days later, Caleb was well enough to be transferred out to the 6-bedder wards. We were so happy to be able to see him and initial blood tests seemed to be trending in the right direction. As only one parent was allowed at a time, my husband and I did 12 hour shifts. It was only for a few days anyway and we wanted Caleb to be with someone familiar. The wards were uncomfortable, to say the least. 6 children meant a lot of crying, screaming, loud noises and worst of all, viruses. Caleb could not rest well with all the noise and after a day, started to get a fever. We monitored him closely and tried our best to get updates from the doctors, who only rounded the wards once a day in the morning.
It was almost four days in the ward and according to the initial timelines given to us, we were supposed to get discharged soon. We kept asking when we could go home, but the answer was always the same. The doctors were still monitoring his blood tests before deciding. We were half packed to go home soon from the hospital and I was on night duty as usual. There was a routine of doing the nebulizer and his medications.
Suddenly, at 11pm, a nurse came in and spoke to me in Mandarin. I caught the main message: Caleb was supposed to go into surgery tomorrow, so he had to fast from 2am onwards. But.. wait a minute? What surgery? We were supposed to be discharged and cleared to go home soon. What was happening? Did they get the wrong patient?
My confusion on the situation was apparent on my face. However, the nurse thought that I did not understand her instructions. She asked to call my husband, who had a better command of the Mandarin language. I knew at this point that he would likely be asleep but I got my uncle to wake him up. I needed someone who could ask the details and get to the bottom of this. After a long ten minutes of my husband speaking to the nurse and then to the doctor, we were notified that Caleb had to go in for a second surgery, scheduled for the next day. We were shocked. The doctor mentioned that Professor Mei would brief us in the morning and give us more clarity.
During the briefing, Professor Mei mentioned suspicions of Caleb having cholangitis, which meant that his bile duct system was inflamed due to an infection. His bile flow was not great and his bilirubin levels were still high, and if we did not proceed with this second surgery, his fever would not come down and the infection would not clear. The second surgery was to add an external diversion on top of his internal diversion. The external diversion from China was different from the ones we knew from the Western world. Instead of a stoma bag, they would insert a tube through his belly button. Every day, we extract the bile out twice a day through a catheter. As parents, we were overwhelmed at this turn of events and the speed of decisions was dizzying. It did not seem like we had a choice on the second surgery as there was no alternative way to get Caleb’s fever down or reduce his bilirubin levels. Again, we went back up to the operating theatre with Caleb.
Our hearts were heavy with worry as this second surgery was unexpected. There was no time to digest our emotions. The second surgery took another two hours and this time, we were advised to leave Caleb in the ICU for the whole week of recovery before we flew home. We changed our flights to accommodate a later date. There was nothing much we could do for Caleb while he was in the ICU and we tried to get updates when possible from the doctors.
Nearing a week in the ICU, we asked the doctors when exactly we could bring Caleb home, but the news was not positive. With the second surgery, the bilirubin levels should have dropped significantly to almost normal levels. Bile would ideally be extracted out at reasonable amounts daily through the catheter. However, his bilirubin remained high. Very little bile could be extracted out through the external diversion. This meant that there was something else internally that was causing his bile flow to be blocked. The solutions from both surgeries were not working. Worst of all, during the surgery, there was a liver biopsy done and Caleb’s liver was not looking good. The damage was already at Grade 3, and Grade 4 was when the liver would stop working. Professor Mei was worried about Caleb in his current condition. She strongly advised us to fly to Shanghai instead of heading home, to seek further advice from a world renowned liver transplant team there on whether Caleb needed urgent liver transplant.
Things were spiraling so quickly. There was no time to stop and really process anything. Before we could even decide, the Beijing hospital team had reached out to the Shanghai hospital, making the arrangements for us to fly over for an assessment. The Beijing side was extremely cautious, making sure we had ambulance rides to and from the hospitals in both cities. We canceled our return flight to Kuala Lumpur, as we did not know how long we needed to stay in Shanghai. We were lucky that we decided to apply for visas, which allowed us to stay for a maximum of 6 months in China. All our plans were up in the air. Caleb was quite weak after two surgeries, and even more yellow and jaundiced that he was before the surgeries. We were extremely worried and hoping for the best. Honestly, we were quite traumatized with the Beijing hospital experience and we just wanted to go home.
The Shanghai hospital was a world of difference. It was also a public hospital but this particular block was recently refurbished to serve as an international liver transplant center. It felt even nicer than our private hospitals back in Malaysia and best of all, the doctor whom we communicated with was from Malaysia! We were so glad to have a doctor who spoke in English and he was really responsive on WeChat. Dr Yang welcomed us on a Saturday and showed us to our double room. We had our own bathroom! I was so happy I could cry. Caleb was a patient on one bed, and my husband was a patient on the other.
Both my husband and I were patients this round as we had to undergo tests to check for suitability of being liver donors for Caleb. The liver transplant can only be done with a living donor for overseas patients. As the liver is an organ that regenerates, the donor was usually one of the parents. The beds were much bigger than the Beijing ones and I could easily fit into a bed with Caleb for the nights. This hospital also had working relationships with our hospital in Malaysia, as many patients were sent over from Malaysia to Shanghai for liver transplants.
We immediately felt more at ease. Gone were the days of not being able to communicate with the doctors. Here, the doctors came at least twice a day and we could reach Dr Yang directly on WeChat. The nurses couldn’t speak much English, but the Mandarin in Shanghai was much easier to understand than the accent in Beijing. The number of patients were much less, which meant the nurses had time to be more patient and understanding with our limited Mandarin. Over the next couple of days, we did blood tests, CT scans, MRI scans, ultrasounds and more. After assessing Caleb’s condition, Dr Yang said he was stable and able to fly home. His liver, while not great, would be able to hold out for a couple more months at least.
We were advised to proceed with the liver transplant as soon as possible though, as the bilirubin levels for Caleb were extremely high. He was also really itchy and quality of life was a huge consideration, given the fact that a transplant was not avoidable anyway in the near future. My husband was the more suitable donor.
After a week in Shanghai, we booked our flights home, just in time for Chinese New Year. We would compile all the documentation needed for the liver transplant back home and send them over for approvals. The approvals would take a few months, as it had to go through both the Shanghai state government and the National Health Ministry in China – tight processes that ensured that the sales of organs were stamped. We were just very happy to be flying home at long last, after an emotional few weeks in China.
I liked that we had a plan: once approvals were done, we would fly back for the liver transplant.
2.5 Years
The approvals took us four months. In that time, we managed to make sufficient preparations for our upcoming trip back to Shanghai. We knew that we would be staying for a month or two this round, as the transplant was a major surgery. Caleb needed at least 3 weeks of recovery time before he would be fit to fly home. Work arrangements were discussed and we would be on unpaid leaves for a while. We had a little dog at home so we sorted out care arrangements with my sister. Leading up to the surgery, we had biweekly checks at the hospital to ensure that Caleb’s liver was doing okay. Our focus was to let him gain as much weight as he could. Weight loss was expected from the surgery, so any weight gain would hopefully make his post-surgery recovery faster.
We were incredibly grateful for our families; they kept us strong and steadfast while we planned for Caleb’s transplant journey. Cost was another worrying factor for us. The transplant alone was estimated to cost us RM150,000, if there were no complications. We had already spent RM100,000 in December from our month in China previously, and with the unpaid leaves piling up from this trip, we were worried about our finances. We knew we could not qualify for a full grant for the transplant, as we were both working with decent salaries. When we reached out to a foundation for help, we were blessed to have gotten RM60,000 in donations from the public within a few weeks. This amount would be incredibly helpful for us, as medication post-surgery would also be very costly. We vowed to return the favour and help other families in need once we stabilized our finances.
In May, we flew back to Shanghai for the liver transplant. My in-laws flew with us to help with errands post surgery. My parents were supposed to fly in a few weeks later, to help us with the second month if we stayed on for that long. This time around, we knew exactly what to expect. Both the hospitals in Malaysia and Shanghai had briefed us on the surgery and all the procedures, tests and follow-ups. It was going to be a long road ahead, with constant lifetime check-ins back in Malaysia to ensure that Caleb and his new liver were doing okay. Mentally, we were a lot more calm and prepared, having spoken to some parents of kids who had undergone transplant and understanding how life changing a transplant could be for Caleb.
Dr Yang greeted us at the hospital. The liver transplant was scheduled for 3 days later, with some baseline tests to be done before that. Everything went smoothly and even Caleb was quite calm in the hospital. The day of the surgery came quickly. It was a really long one; 7 to 8 hours in total. At 8am, Caleb and my husband, who was the donor, were wheeled into separate operating theaters at the same time. One group of doctors would operate on the donor and extract out 20% of my husband’s liver. At the same time, the second group of doctors would operate on Caleb and remove his entire liver. Once the donor’s liver has been extracted, it would immediately be inserted into Caleb as his new liver. The liver is the only organ in the body that regenerates, and within 6 months, both the donor and recipient’s livers would have grown back to the sizes that are needed for bodily functions.
I kissed my husband goodbye and stayed with Caleb, whom I had to accompany downstairs to the operating theater. I was glad that I was not alone for the wait as my in-laws provided a lot of moral support. The doctors were slightly worried about adhesion for Caleb’s surgery, as any prior surgeries would leave scar tissues and potentially cause organs to stick together. As the doctors cut through the layers to reach his liver, if adhesion was really severe, there would be risks of excessive bleeding during the surgery or damage to some of the organs. It was going to be a long day ahead, but I knew that both of them were in the best hands.
Just slightly past 11am, 3 hours into the surgery, Dr Yang came out to show me Caleb’s native liver. It was huge: as big as two palms of my hands, which was surprising to me as Caleb was only 9kg. The liver was a mix of dark red and black, whereas a healthy liver should be light red in colour. At noon, my husband was out and moved back into our room for recovery. He was groggy and in pain, with an expected recovery time of a week. After a week, he would get discharged as a patient if all was well. For Caleb, there would be a week of monitoring in the ICU after the surgery. Similar to the Beijing hospital, we would not be able to see him during this week. Once Caleb was stable, he would then move back into our room for the remaining few weeks before we could fly home.
Finally, at 4pm, Caleb was done with surgery. Everything went smoothly and according to plan. Relief flooded through me, together with a deep sense of gratitude for my husband, the doctors and our amazing support system.
China was a country that believed the fastest way to heal was to move and walk around, instead of relying on painkillers. After two days of bedrest and IV painkillers, my husband had no oral painkillers prescribed by the hospital. We bought some Panadol, which he took for the painful nights. It was amazing to me that the painkillers were cut off so abruptly for patients, as I remembered vividly being on oral painkillers for a week after my C-section. My husband slowly but steadily started gaining more strength and mobility. By the end of the week, he was moving around on his own. Caleb was also recovering well in the ICU. Dr Yang kindly sent us videos daily and during his ward rounds, he would tell us that Caleb was behaving so well in the ICU.
In the rooms next to us, we realized that there were two other Malaysian children who were also undergoing liver transplants. Our three families bonded over the shared experiences. We understood a bit more about the different liver diseases that brought each of our families to Shanghai. It felt so nice to chat about common topics, with all of us heading back to the same hospital in Malaysia for follow-ups. Each child had different complications and symptoms, but as parents, we all went through the same arc of trying to avoid transplants, and years of medications and hospital visits. It was an unspoken bond formed by worry and uncertainty, both from past events and imagining the future of our children post-transplant.
After 6 days of ICU monitoring, Caleb moved back into our room. He was energetic and happy, with an itch that was minimal compared to pre-transplant times. Caleb looked so much better than his condition in Beijing. Despite a long scar across his belly, he was active and moving around. I was amazed at his pain tolerance, but at the same time, he must have been enjoying the lack of itch that used to blur all his senses. Week by week, his recovery was strong. His blood tests finally showed a normalization of the bile acids and bilirubin levels (never before since he was 3 months old), with his skin visibly becoming whiter as the weeks went by. We expected to stay in Shanghai for 6 to 8 weeks this time, but in the end, we were cleared for discharge in 3 weeks! We were eternally grateful for the Shanghai team’s care. Our Beijing experience made us feel like a lonely ship out in a rough storm, but this time around, Shanghai was a big, steady ship in calm waters.
We were asked to check into the hospital in Malaysia as soon as we landed. A short 3 day stay at the hospital assured us that everything was good in terms of Caleb’s recovery. We could finally bring Caleb home! We were very blessed to have had a smooth sailing recovery journey post-transplant, as we knew the other children had complications that kept them in both Shanghai and Malaysia hospitals for much longer.
Caleb was a changed child. He could now sleep peacefully at night, which meant we could finally get full nights of sleep as well. Because he got enough sleep, his days then became a lot more play-based instead of nap times. The challenge was different, having to figure out activities and ideas to occupy his time for the whole day. Caleb picked up many of his motor skills quickly and has progressed so much in terms of his ability to independently perform tasks on his own. His laughter and smiles filled the air, along with the occasional tantrum – a hallmark of the terrible twos. We loved every moment of it. This was what it felt like to raise a normal, healthy kid. It was, and is, a remarkable turning point for our whole family.
Hospitals are still a part of our routine, as were medicines. We are currently 3 months post-transplant. Caleb has so many different kinds of medications: immunosuppressants, antibacterial, antiviral, antifungal medications. On top of that, he has iron and vitamin supplements due to deficiencies. We have a total of 8 different medications and supplements to feed him daily, but he takes them like a champ. Blood tests are weekly and we have to be under close monitoring to adjust medication dosages when necessary. Too much of the immunosuppressants will be toxic for Caleb; too little and we face the risk of his body rejecting a foreign liver. Caleb understands words a lot better, and has managed to overcome his fear of doctors and nurses. He now allows the doctors to check his body at every visit, when previously, he would start crying when we entered the doctor’s room. Hospital visits and medications will become less over time, but it will be a part of Caleb’s life forever.
It is a small price to pay in exchange for Caleb’s quality of life now. His warm smiles remind me to be grateful everyday. We know that not every family that went to Shanghai returned successfully. Some of the children’s stories broke our hearts. We keep them in our prayers and we think about their families. We hold Caleb that much tighter knowing that we are blessed to be able to go through the post-transplant journey together.
With space to breathe and a clearer mind from sufficient sleep, my husband and I can think about things that we had parked aside before. We speak about schools and his education. We dream about vacations in various destinations. We talk about potty training – a phase we know is notoriously difficult for PFIC patients because of the itch. It feels so good to discuss topics that are not unique to Caleb’s condition. To see him grow and be on the same track as all the other kids is a privilege.
My hope for Caleb is for him to live a long life full of happiness and health. Most people say that he will not remember the surgeries and the itch because he was too little, and I’m grateful for that. His little double chin and chubby cheeks remind me that a healthy life is the enabling factor for anyone to enjoy life. I cherish his hugs and kisses, and the times when he comes over to me and holds my hand. Our journey has taught me strength and resilience, but also immense gratitude for each moment. There is so much I want to experience with our little family. The best is yet to come.
A huge thank you to Germaine and her family for sharing this story.
My grandson Leonardo showed symptoms (jaundice, pale stools, dark urine, irritability, and trouble sleeping) when he was three months old. He received a preliminary diagnosis after seven days in the hospital and a battery of tests. It was only confirmed months later through genetic testing. My daughter suffered a great deal. She had panic attacks while Léo was in the hospital and traumatic stress after the diagnosis. We all suffered.
But I knew I had to be strong so I could help her, even though inside I was desperate. Not a day goes by that I don’t think about what tomorrow will bring and how Léo will be doing. Our hope is that he will be able to get access to the high-cost medication so he can have a better quality of life.
I want people to know that even if a child looks healthy, that doesn’t mean they are well, and that parents need help and support. PFIC has treatment, but access to medication, at least for those of us living in Brazil, is a painful struggle and still far from what it should be.
-Silvana, Leonardo’s grandmother
O Leonardo meu neto apresentou os sintomas (inctericia, fezes claras, urina escura, irritabilidade e dificuldade para dormir) aos três meses de nascimento. O pré-diagnóstico se deu com sete dias de internação e uma bateria de exames. Só meses depois foi confirmado com o mapeamento genético. A minha filha sofreu muito, teve crises de pânico durante a internação do Léo e estresse traumático após o diagnóstico. Nós todos sofremos. Mas eu sabia que teria que ser forte para poder ajudá-la. Mas por dentro eu estava desesperada. Não tem um dia que eu não pense em como vai ser o amanhã e como o Léo vai estar. A nossa esperança é que ele consiga ter acesso a medicação de alto custo, para que ele venha ter mais qualidade de vida. Eu queria que as pessoas soubessem que mesmo que a criança aparentemente apresenta estar saudável, não é sinal de que ela esteja bem e que os pais precisam de ajuda e de apoio. Que a PFIC tem tratamento, mas que o acesso a medicação pelo menos pra quem mora no Brasil é sofrida e ainda muito distante de ser digna.
I started to have symptoms of illness PFIC2 since l was a baby. There was itchiness, insomnia and also other symptoms with the passing of the years. My doctors in Albania could not find a diagnosis.
When l was 8 years old l went to Italy. The doctors there did not give me the exact diagnosis and cure. They told me l had PFIC3. The moment l received my diagnosis and cure and diet, l felt that l wanted so much to sleep for hours. l thought that finally my itchiness will go and l will be able to sleep.
Now I have a diagnosis, a cure and a diet which l took in April 2023, when l was 24 years old. However, I have struggled to live in a calm environment with healthy people. This has made it difficult for my condition to stabilize. I want so much to live a healthy life. I want the families, friends and people around us to know more about PFIC, because living with symptoms of PFIC can be so hard and exhausting, let alone being able to build a healthy and happy life.
Blake was a normal happy baby. His symptoms suddenly arose at 7 months, with extreme jaundice, itch, and sleep problems. One visit to the pediatrician turned into specialist visits and countless blood draws. After 3 months of worry, Blake finally received his PFIC-1 diagnosis at just 10 months old.
The year following diagnosis was busy. He had lots of visits with his hepatologist, who prescribed every available medication to help with itch. Unfortunately, none worked, and Blake was listed for liver transplant in May 2024 at just 2 years old. Blake received the Gift of Life from his deceased donor on July 31, 2024.
While that immediate period was filled with worry and stress, we were extremely thankful and indebted to our donor girl’s family. Fast forward nearly two years, and Blake is a thriving 4 year old who enjoys playing outside with his big brother and twin sister. We are thankful for the PFIC community and Gift of Life Michigan for all the support along the way!
What is your diagnosis? And when were you diagnosed?
I was diagnosed with ABCB4 disease (PFIC Type 3) in April 2025, at age 38. After 20 years of unexplained symptoms, I finally have answers.
Think back to the time before you were diagnosed. What symptoms were you experiencing? How did it affect your life?
My symptoms started when I was just 12-14 years old with a severe virus that left me exhausted and anemic. But doctors never really investigated what was happening. At 19, I took Lamisil for a toenail fungus, which caused liver problems. That same year, I developed shingles and was in a car accident. At 24, I lost my gallbladder due to stones in my bile duct.
But things really escalated between 2022 and 2025. After complications from a myomectomy, I became severely anemic and needed two bags of blood. My GGT levels shot up over 800. I lost weight rapidly – dropping from 136 to 112 pounds over 53 weeks. For months, I underwent procedure after procedure trying to find answers: ERCPs, liver biopsy, MRCP, colonoscopy. No one could tell me what was wrong.
How are things different since your diagnosis?
Everything changed when genetic testing identified a heterozygous ABCB4 mutation – actually the fourth variant ever identified, from a 1999 research paper. There are only 8 other genetic donors registered with this mutation. My local provider diagnosed me based on my clinical presentation and genetic results, even though the genetics company marked it as “unknown significance.” I’m now on 1,500mg of Urso daily, and I’ve seen significant improvement.
I also connected with Dr. Catherine Williamson at Imperial College London – she wrote the original research paper on this mutation. She validated my diagnosis and helped me understand the broader disease associations. I’m now under the care of Dr. Vilarinho at Yale, enrolled in genetic studies and signed up for medical research.
How has your diagnosis/condition affected your family?
Understanding my diagnosis has helped me see patterns in my family that make sense now. My grandmother had a liver transplant at 61 and died at 70. Her mother had 18 pregnancies, and half of those babies didn’t survive infancy. All of my grandmother’s adult siblings had their gallbladders removed as teenagers, and most developed liver cancer. I recently found out I have a second cousin with both liver and kidney transplants.
These patterns suggest a genetic component across multiple generations that we never understood before.
Tell us about your treatment journey.
My disease pattern is progressive flares triggered by viruses. Each flare takes months to years to recover from. I’m concerned about the future based on my family history – so many developed liver cancer. But having Dr. Vilarinho’s expertise and being part of research gives me hope that we’re monitoring things carefully.
Where have you found support?
I’ve done extensive research – I’ve read every scientific article on JSTOR about ABCB4. Knowledge has been powerful for me. I’ve also connected with other patients online and found it validating to see others with similar symptoms asking the same questions I had before diagnosis.
Do you believe your condition is well understood?
Not at all – by either the public or many in the medical community. Even my local GI doctor, who is wonderful, now has a whole folder of ABCB4 research articles because this was so new to him. The validation aspect of finally being diagnosed was huge. After years of procedures with no answers, someone finally believed me and could explain what was happening.
What’s one thing you would say to an adult who received a similar diagnosis today?
Don’t give up on getting answers, even when genetic reports say “unknown significance.” If your symptoms match what diagnosed patients experience, keep advocating for yourself. And find doctors who will take the time to really understand – my local GI and Dr. Vilarinho have made all the difference by being willing to learn alongside me.
Erin lives in Georgia with her husband Jay, where she works as a project coordinator for a nonprofit and co-owns a real estate photography business. She is passionate about raising awareness for adult cholestasis and helping others navigate the complexities of genetic testing and diagnosis.
We are a family from Serbia, and this is our story of struggle, fear, hope, and unconditional love.
Our older daughter was diagnosed with PFIC type 2 when she was only four months old. At that time, she was the only recorded case in Serbia. Everything that followed was unknown, frightening, and overwhelming. When she turned one year old, we traveled to Italy for a liver transplant. The surgery lasted 11 hours — for my husband and me, it felt like 11 years. Every single minute felt endless.
Thanks to the incredible doctors and medical staff, our daughter is today a healthy child. She goes to kindergarten, attends ballet classes, and is joyful, curious, intelligent, and full of life. Looking at her now, it is hard to believe what she has been through.
Three years later, we decided to give her a sister. Sadly, fate was cruel — our younger daughter was also diagnosed with PFIC type 2. She is now two years old and faces a very difficult daily reality. The itching is so severe that she wakes up at night covered in blood from scratching. Watching your own child suffer and not being able to immediately take the pain away is something that cannot truly be put into words.
However, a week ago we were given a ray of hope — the medication odevixibat was approved, and our younger daughter will be the first child in Serbia to receive it. We see this as a new chance and a new beginning.
We do not lose hope. We are here for our girls 24 hours a day, surrounding them with love and strength. With our heads held high, we move forward, hoping that this agony will soon come to an end and that we will finally be able to enjoy their childhood without fear — the way every child deserves.
On a summer night in June 2023, Liam woke up to a persistent nosebleed that lasted over 45 minutes. Concerned, we decided to call 911 for medical help when Liam started vomiting blood. Emergency services were called, and upon arrival, Liam’s bleeding nose had stopped, and he was alert. They cleaned him up and his parents scheduled a visit to his primary healthcare provider the following day.
During the primary doctor’s visit, Liam appeared fine, which led to the doctor stating his symptoms occurred due to seasonal issues. However, his family persisted in requesting blood work. Reluctantly, the doctor agreed, which eventually revealed concerning results. Urgently, Liam’s parents were told to bring him to Children’s Hospital of Philadelphia (CHOP) for further evaluation.
At CHOP, Liam underwent extensive testing as doctors explored various possibilities, including Leukemia and Lymphoma, which were both ruled out. After a week of hospital stay and numerous tests, Liam’s case took a complex turn. As the Fourth of July weekend approached, we were shifted to outpatient care due to limited medical staff availability.
The medical mystery surrounding Liam continued with appointments, ultrasounds, and genetic testing. A long wait followed until genetic testing revealed a diagnosis of PFIC-3 in March 2024. Subsequently, Liam’s sister was also tested and diagnosed with PFIC-3 along with Alpha-1 AT deficiency.
Now, we are navigating medical interventions for both children to determine the course of action and the potential need for liver transplants.
Inabiyah Pari was diagnosed with PFIC 2 when she was 8 month told.
“She was jaundiced since birth and after a lot of tests and a biopsy we had no answers. With the help of genetic blood screening she was confirmed with PFIC 2. It was like a sky falling on us because she was the most precious thing in our lives and we are living Far away from our family and friends.”
Inabiyah Pari is from Sydney, Australia.
“Thankfully with the support of our doctors, nurses and friends we overcome that shock and we are very hopeful in This journey.”
Sophie’s timeline is a little different as her story starts with her and not her child. When she was 16 she started getting sick and at 19 they realized she had gallstones. When she was pregnant she also had obstetric cholestasis. These were both signs she was a carrier of PFIC. She never knew why she was sick and had gallstones at such an early age and she found it odd that the doctors never looked into it further.
When her daughter Eva was born she was very thin, her liver levels were completely off and she was in the hospital over and over with “failure to thrive”. She was not growing, her salt levels were low, and she was not absorbing any nutrients either. The doctors said that her liver levels would regulate, that it was common for babies to experience bouts of irregularity but Sophie had a feeling that they were wrong. The obstetric cholestasis Sophie experienced was her first clue. Sophie joined a facebook group for mothers with obstetric cholestasis asking what could be the cause. Finally another mother responded saying that there has been a link to two different diseases. One of them being PFIC.
Sophie began pushing the doctors to do some tests on Eva and they found that she did in fact have PFIC 3. It took 9 months for Eva to be diagnosed though it would’ve taken longer if she didn’t push them to do the tests. Even then, to get the genetic sequencing results for themselves it took 6 months. Sophie’s husband has the normal PFIC 3 mutation and Sophie has a varied version of the same mutation. Sophie did not know she was a carrier until Eva was diagnosed. She said that the doctor told her that her gallstones at such a young age should have been investigated further especially since they had been in her family for a few generations. She has been referred to have some liver tests now to make sure her liver levels remain normal after having obstetric cholestasis during pregnancy and her liver levels being so up and down.
One of the main symptoms of PFIC that Eva experienced was poor nutrition, which doesn’t get talked about enough. Eva Wren had nutrition issues and they did not know if it was allergy related, PFIC related, or both with the potential of food allergies related to PFIC. Eva couldn’t keep any food in her. She had constant diarrhea and threw most of her food up. Nothing seemed to help and she wasn’t getting much better as she got older. Finally, Eva started on ursodeoxycholic acid and since then Sophie said that Eva has done a complete u-turn. Eva was so thin up until she started on this medicine that she was “skeletal”, but since starting the medicine she has been putting on weight. Sophie even took Eva to the hospital for a check-up a couple days before our call and the doctor said to Sophie that she “has to watch Eva because she is ‘getting too fat.’” This is a major win! It could have seemed hopeless for the Bourton’s that Eva wasn’t going to get better when she was “skeletal” and not retaining nutrients, but they stayed positive and kept looking for something to help. Finding a drug or treatment that changes your life could be possible and the Bourton’s found just that.
They don’t know how long this will last as there is scarring on her liver. But they have had a year now where they have had relief from PFIC. She has been able to go to nursery and be a normal child. They are hoping for the best as they move forward with ursodeoxycholic acid.
I asked Sophie how she felt when the diagnosis finally came through, and her response was just like any mothers would be; “I just felt like there weren’t any options available to us. I felt sad but more so frightened for Eva. It was a domino effect where I was frightened for Eva, then frightened for us with our jobs and financially.” Sophie also mentioned that she felt hurt from people not helping them when they needed it most and that it was hard to move on from that. The pandemic, as I am sure many can relate, made it hard to cope. A lot of the coping mechanisms like seeing family, traveling, getting out of the house were all taken away at the same time.
Sophie wants Eva’s story to be a ray of hope to show other parents that there is potential in things getting better, and with research improving over time. Eva’s story has shown this so early in her life.
A Strong Advocate
Sophie has been a very strong advocate for PFIC, especially when there was a push to get the drug (Odevixibat) approved by NICE in the UK. Sophie has also joined in on the PFIC Awareness Day campaign, shared photos of Eva and now has shared her story! We are very grateful for such strong advocates. When I questioned why she advocates, and on such a high level, she said it was because she knows how important it is to spread awareness, especially for a disease that no one really knows about. Sophie told me “I was actually relieved to receive a diagnosis. When you are a first time mom, other moms can be really dismissive. Saying ‘oh yea my baby was skinny, my baby was small, my baby was this…’ and they didn’t understand the extent to which Eva was actually sick. With covid people couldn’t see her, so other people would say ‘yea don’t worry about it’ but they didn’t understand.”
Another question I posed to Sophie was “What else, other than being a parent of a child with rare disease, pushes you to put in the work, be an advocate, and share your story?” Her reply “I think really it’s just desperation to improve things for Eva. Whether it’s raising money, pushing research, or getting the drugs approved. I just want to help her, and then even if one person is helped get a diagnosis because of what I have done, posted, or said then it was worth my time.” Sophie also said that she can see why it is hard for parents to do the advocacy work, when your child doesn’t sleep through the night, is itchy, is still sick every day, it is almost impossible to do advocacy work. Now that Eva is well, Sophie wants to make the most of the time, and do as much as she can while she has the time.
The Bourton family was also another example of utilizing the financial assistance available for families affected by PFIC. They ended up using the Children’s Liver Disease Foundation, and received financial assistance through them, and as Sophie put it “that really saved our bacon.” If you are in need of financial assistance, it never hurts to ask. We have our financial assistance program set up to help families in need and all you have to do is apply.
I finished the interview asking the same question as all the other interviews. What is one thing you want people to know about PFIC patients? Sophie answered “I want people to know that it’s not just a liver disease, it affects every part of the body. I think people underestimate how important the liver is and it causes all of the things from nutrition to development, anywhere from size to eyesight.” I thought this was an amazing answer, and it was one I had not heard before.
It was a lot of fun getting to know Sophie and Eva’s story, as well as hearing all of the input she had on the disease, the network, and staying positive with a rare disease. Thanks Sophie! I hope everyone enjoyed this edition of Story Sunday and got a positive message from such a positive person.
Chandler is 3 years old, 2 months post transplant, and only found out he had PFIC last September. The road to having a liver transplant happened very quickly for the Smith family going from not knowing he had PFIC and knowing about the potential for a liver transplant, to learning the name of the disease and being told he needed transplant within the next 6 months. 3 months later in December of 2021 Chandler would have his liver transplant.
I asked them what kind of PFIC that Chandler had, and they didn’t have a clear answer. They were told that he has PFIC syndrome, but could not narrow it down to one of the PFIC types or subtypes that have been seen. Meaning that it was not showing up genetically, but all of the symptoms were present.
They knew from Chandler’s birth that he had something wrong with his liver. He was born 7 weeks early and was in the NICU for about a month, and while there they noticed he had elevated bilirubin. At the time, they believed the liver issues were akin to being premature. At 5 weeks he had a biopsy to check for biliary atresia which came back negative but the signs were there that his liver was not working properly. Chandler also had the itch. His itchiness was moderate to severe. He would scratch his ears until they bled, Leah kept his nails short so he didn’t cut himself, and he would sway back and forth in his seat to scratch his back or belly. When I asked about his sleep, they said at first the itch affected it a lot, but for a while they attributed it to him being premature. Though later they would realize it was because it was itchy. They ended up trying hydroxyzine and it worked! Chandler started sleeping through the night and his itchiness was bearable.
For the longest time they did not know what Chandler was experiencing. They were only ever given the names of the symptoms that Chandler was having. They did not know he had PFIC until they learned of a drug trial to combat liver cholestasis at Georgetown. The doctor immediately told them that he needed a transplant. From viewing his labs, and after seeing him in person, they knew. Leah said that “sometimes you feel a little silly when people ask what your son has, and you have to answer with ‘I don’t know’.” They finally had a name for the disease that was causing their son’s liver to fail. Chuck made the comment “I felt a sense of relief. There were so many complex terms, and symptoms. It was hard to understand and repeat to others. But when I learned it was called PFIC, that’s so simple! There was a name for this disease and it isn’t so vague anymore.”
At only 1 year old, Chuck and Leah were told that Chandler would need a liver transplant. Leah said for them “It wasn’t a question of ‘if’ Chandler would need a liver transplant, but ‘when’. Would it be 3 years? 5 years?” A year later it was time to find a donor. After their conversation with the doctor at Georgetown, they knew it needed to be sooner, and 3 months later he had his liver transplant. Chandler is now 2 months post transplant, and is in great spirits. He is running around, playing, and as his mom said “You would never think anything is going on with him.” Liver transplant is not a cure however, as I am sure many of you know. Even though Chandler is running around and playing there are always the what ifs like complications, liver enzymes rising, the return of the disease. Chuck mentioned that Chandler may say “my tummy hurts” or have diarrhea one day and they don’t know whether he is just being a toddler or if it is something with his transplant. Not to mention the 12 medications he is on to help his body with the transplant.
After the transplant they thought that finding other families that had children who received liver transplant would help them find some clarity on the what-ifs of transplant. The other family they talked to did not have a PFIC kid but they did have a lot of great insight and provided some comfort to the Smith’s. They knew that the worrying would never stop but they could have a little piece of mind. This continues to show how important connection is, and how finding people with a similar challenge as you can make everything seem much less daunting. Leah had a great insight into what other parents can do for self-therapy while Chandler was going through PFIC and liver transplant. She had put together a blog for herself to use as an outlet or talk about the experiences she was going through and the struggles. Not only was she using the blog in that way but she said that it would also be used for Chandler to look back on when he grows up to see what he went through and understand a little better. The third reason she mentioned was for other families to see. To show that it is very scary and overwhelming, parents have so many questions, and she was hoping that her blog might be a good realistic source. See the blog here: https://chandmantough.weebly.com/.
We met the Smith family through our financial assistance program. They applied recently and we were so excited to help them get rid of a few outstanding bills. This is exactly what our financial assistance program is designed for. Chuck found out about our financial assistance program the first time he went to our website when he was trying to learn more about the disease. He didn’t look into the financial assistance until he thought they were ready to sit down, get organized, and ask for the assistance. There was also a factor of feeling comfortable enough to ask for help. They received assistance from a social worker to look into fundraising through their close friends and family, and through an organization called COTA. Unfortunately, fundraising is hard, and asking for money to support a child whose disease isn’t well understood can be daunting. It is hard to let people know your personal financial situation as well. People may see a family and think they don’t need the money, but they don’t know what comes with a rare disease, or the burden that comes with liver transplant and just how high the costs can be.
One of the best parts of the conversation we had was about insurance, taxes, and financial planning. Even if you plan for these things, you can never really plan for these things. Who could plan for multiple thousands of dollars in extra costs per year? Between the piles and piles of medical bills, getting bills from the hospital and different departments, finding out what insurance covers and doesn’t. All of this combined can make things seem impossible. The one message Chuck gave for all of this was to “Stay organized, try to learn as much as possible, and to stay positive about it. Everything will be ok.”
The final question I asked them was the same question I have been posing to everyone. “What is one thing that you would like people to know about PFIC patients?” Leah answered “Even though Chandler has had this disease from birth, he is still a normal little kid, and he is no different from anybody else.” Chuck responded “These families are going through a lot of stress, and you may not know it because they try not to show it.”
At the beginning, before we even knew Kennedie had PFIC 2, she was outrageously itchy and we had no explanation as to why. It was a terrible feeling having doctors ask why she was covered in scratches and scabs, and if everything was okay at home.
After her diagnosis, she was on three different medications for the itch and it still didn’t stop it. We had to keep her in long sleeves and pants even in the middle of summer. People would ask why we didn’t just give her Benadryl for her itching. People don’t understand that the itch is from deep inside their bodies.
We would give her cool baths to give her some relief. I was afraid she would scratch her stomach and pull out her g-tube in the process. As soon as she had her transplant the itch was gone. It was an immediate change and she has been able to wear anything, and more importantly, sleep through the night, which she hadn’t done in her entire life. Transplant can cure the itch, but should never be the only option.
Cedar was diagnosed with PFIC 2 when she was 5 months old. We were traveling visiting family in Wisconsin when she developed random bruises on her back and a swollen shoulder out of nowhere. We took her to the ER and she was in full blown liver failure. Nobody could understand why, but they were able to stabilize her and we were sent home to Kentucky to wait on test results.
After one month went by, in and out of the hospital, genetic testing came back and she was diagnosed with PFIC 2. She was jaundice, super itchy, and she cried all the time. Her doctors started her on a lot of different medicines including ursodiol and vitamin supplements. After another month she was started on Rifampicin because her itching was out of control. We used to have to keep her covered from head to toe because if there was any bit of skin showing she would scratch it until it bled.
The Rifampicin did help “take the edge off,” but when she was 15 months old, the itching was still so unbearable that her doctor recommended surgery. At that time there were no trial drugs that were available, so she had a partial external biliary diversion (PEBD). At first, it didn’t really work. We had been hoping for relief, but now she was very itchy and had an ostomy bag that she was always scratching off of her belly. But we all adjusted and it was manageable, and after about a year her itching did finally get better, actually became non existent. Whether she grew out of it, adjusted to it or the bag finally did help to control her bile build up we’re not quit sure, but it was much better.
Things were finally going very well for the first time since she was diagnosed at five months. We still kept a very close eye on her. We traveled two hours to see her specialist every three months to check in on her with labs and a liver ultrasound. Unfortunately, at age 5 we started seeing more signs that her disease was progressing. Her spleen was becoming enlarged, which started to trap her platelets and other blood cells, her vitamin levels became chronically low, so low that she was at risk for complications even though she was on the highest dose of supplements, and she was getting more and more tired during the day. Her liver was becoming stressed and we felt like she was a ticking time bomb. We had maxed out the current available treatment options for Cedar and she was still getting worse, so her doctors and us decided it was time to list her for liver transplant.
We knew that we were making the right decision, however it was extremely hard to accept that this is what needed to happen. That if maybe if she were born ten years from now, there would be medications or other treatment options that could help or cure her. We were grateful that she was able to go five years before she needed a new liver, but it was hard to accept that she would need a new liver at all. With that being said, she was transplanted within 2 weeks of being on the list. She recovered extremely quickly from surgery and we were home within a month. So far, we have had one episode of rejection and one hospitalization for pneumonia, both went very smoothly. She has a mild form of the post transplant complication AIBD, but we will just take that as it comes.
After we saw the picture of her old liver (in the pictures above), we knew we made the right choice. It’s hard looking at that picture and wondering what would have happened if we waited. We still wish that her disease were curable and that she never would have had to go through this, but it is what it is at this point. She is currently happy and full of life, and we couldn’t ask for anything more.
Three weeks after Anna was born her skin became yellow. Our pediatrician sent her blood for analysis. Her results were not normal, so he told us to consult Prof. Richard Thompson at Kings College Hospital in London. At King’s she had a liver biopsy and genetic test done. After 2 months we got the diagnosis – it was PFIC type 2.
She started taking medicines: Ursofalk, vitamins A, D, E, K. Her blood test results improved, but still were not normal. Her jaundice disappeared, slowly. The symptoms worsened after she turned one. In the beginning she suffered from itching every few days. Rifampin helps the itching temporarily. Then she scratched herself more and more. Nights were worse than days, she woke up every night screaming and it was impossible to calm her down. The hardest thing was not being able to help her. When she was one and half years old we managed to get her into EAP Albireo.
She responded well to that medicine but she still suffers from itching a bit. We really hope at the medicine that she’s taking will allow her to live a normal, happy life. We believe that someday new genetic therapy will be developed and PFIC will be completely curable.
My son was twenty days old when I noticed something was wrong with him. He was very fussy and would cry a lot without any reason. He would poop ten to twelve times a day and poop was oily. We visited a lot of doctors that thought he had colic issues. When he was five months he got jaundice. We visit gastroenterologist who told us he might have pfic 1 or 2. Unfortunately, Pakistan has no facility for genetic testing so for six months, we were very worried. Then Emily Ventura helped us find a way to get genetic testing and at one year old we confirmed our son had pfic 2.
From the first symptom until now we don’t have proper medication in whole of our country like cholestramine and neltraxon. We have to travel five hours to visit our liver doctor and use treatment is also very expensive.
Hardest part of pfic is the itching. I hate to see my son in so much discomfort that he even can’t sleep at night. It’s also heartbreaking to see him get taunted for itching so bad.
A lot of things like experience of people from pfic Facebook group helped me to tackle itching and one member of the group from India told me about an herbal medicine that helped a lot. My son has been using it since one and half month and itching is considerably less, his health improved and his appetite increased, I would suggest to all pfic parents to talk with other parents who have experienced this disease. They help a lot.
Keep your kids cool as itching becomes worse in hot conditions and herbal medicine that is proved good for my son until now after 3 months labs will be conducted and I will post a review of that medicine
We are Francesca and Simone the parents of little Eva Luna. After her first month of life Eva began to grow up little by little, squirming at night and rubbing her little eyes wherever she could. All these symptoms were mistaken for gastroesophageal reflux. We started very strong therapies, but Eva started crying often, it was a heartbreaking cry, especially in the evening. We were told it was colic! But we knew something was wrong, we just had no idea how much. When she was three months old, she became jaundiced, she got diarrhea and we went to the emergency room. We were rushed to hospital, the first three days we spent the nights away from her and Eva cried and we cried with her. One morning we arrived in the ward and found her shaved with a canula on her head, they found no other veins available. I became a difficult mother. One of the doctors told us that many pathologies had been ruled out and that he suspected a genetic reason, he whispered in a low voice the words “progressive cholestasis”.
They moved us to a department where we could stay with her but I became less and less manageable. I read that progressive cholestasis affects one child in 100,000, and I told myself that it couldn’t be us. We kept hoping for a transient cholestasis. We went home but they kept repeating that they were waiting for genetics. The result of genetics came. Progressive familial intrahepatic cholestasis type 1. New and untreated disease.
To this day we cannot find the words to describe what we felt. You suddenly find yourself in total darkness. We only knew that at some point in her life she would undergo a liver transplant. I am not ashamed to say it, I fell into depression, I couldn’t get out of bed, panic attacks became companions of my days. My son Ernesto watched us and in his 5 years he saw his sister taking medicine on medicine and a mother torn apart. Simone became a superhero, he had to manage his pain, protect Ernesto and try not to let me touch the bottom, even today I still wonder how I would have done and how I would still do without him, without his strength. He looked at Eva Luna and felt the joy of being a father, of having her there despite everything, despite the monster was at home. I only saw the pain, but the spirit of survival and above all the love I feel for her, he told me to react and at a certain point I began to see her, she who together with her brother is the reason for life.
Months went by, we started to study, we discovered that type 1 of this disease is basically the worst, transplantation is not resolutive because other organs are involved, intestine, pancreas, short stature and deafness. Yet another blow. We came into contact with other families and with the international Pfic network, there were experimental drugs for itching. Itching that continued to increase day after day. We went to northern Italy where the trials were active but it seems that Eva Luna’s genetic mutations were not compatible with enrollment in the clinical trial. After months of stopping because of Covid, good news arrived, Eva had been enlisted in the trial! Hopefully we start the drug.
Months later we can say that it is not Eva Luna’s drug, that there was no miracle. The itching is taking away everything, it’s taking away Eva who is no longer living her days. She doesn’t sleep more than four hours at night, the rest she spends trying to tear her skin. We try to distract her as much as possible sometimes it works, especially thanks to her brother, a little warrior himself, called to fight a war too big.
She is the strongest and toughest little girl that exists, but we can’t ask too much of her and you tear yourself apart because you can’t help your daughter, you despair. In front of us there are only surgical options with little chance of success. Only RESEARCH could work a miracle. The association Pfic Italia Network was born also for this reason, to give a chance to that miracle.
This event was life changing for me, changed my direction, my approach to PEBD, and parenting a child with an ostomy. It started with something I read on a website, so I want to pass it on to all of you on this website.
When we got the news that Cade was heading to PEBD, like every mom out there, I hit Google. I found a discussion board of people with ostomies (UOAA). I browsed through so many questions and comments looking for something to cling to and show me the way. How were we going to do this? I wanted to absorb everything, or maybe just something.
I came across a mom who said that she planned to make the BEST situation for her young child with an ostomy. She would hide it so well, so no one in the neighborhood, the school or her teammates would ever know. She would keep that ostomy so locked down and hidden…her daughter would be JUST like the other kids! She had cool tricks to hide an ostomy, best products, etc….a perfect plan. This mom was speaking to me. I could relate to this plan.
Then, she went on to say that her daughter went to her very first sleep over in 6th grade– 6 whole years in the same school, and no one had ever known – not the kids, nor parents. Well of course, at that sleepover her bag leaked badly, leaving her daughter mortified and alone. Her friends were confused and parents scared for the next sleepover. No one knew, just like they wanted…. right?
Needless to say, she was passing this lesson forward. This mother strongly warned against doing what she did.
This struck me hard. I was planning on doing the same when Cade hit school age. I thought that hiding it would be how he would have a regular life and be treated like everyone else. Cade is now 16, and this sounds silly looking back, but it changed us. From that moment on, you couldn’t find a person within 50 miles who didn’t know about Cade and his bag. We told everyone! By the time Cade was 5 years old and he entered kindergarten, he was so comfortable with his ostomy that he was showing people (appropriately), and talking about it! He was explaining his disease to those around him. His bag gave him confidence, power and stripped away any shame or stigma. It actually did the impossible, and the exact opposite of what I ever would think… it made him feel just like everyone else. Most kids eventually forgot he even had it.
I have met lots of children with ostomies since and I have learned that for some more introverted kids, this may not be the best path– but for us, it was the BEST decision we ever made, and one worth exploring.
She is my second child. After her birth everything was going fine. When she was about 4 months we noticed that she would scratch her ear and it would bleed for hours. Doctors said that it was just dryness. When it happened again and again, we visited our paediatrician to check her pt/inr which was really very high. The doctor thought that she had clotting issues but fate had other horrendous plans for us.
In her 6 months, she started turning yellow and itching increased to another level. The doctor immediately told us of the liver issue and diagnosed her with PFIC.
We have been dealing with ITCHING since then. We have seen worse days and even worser nights. She will itch with everything and anything. If I don’t let her itch she cries so badly. Nothing seems to help the itch. The itch would make her bleed but still she wouldn’t be satiated. She would itch and itch. Ofcourse there are better days when she will itch less and we would just hope for the next day to be better. Hoping for the good days to be here. It breaks your heart to see your child suffer so so very much. Not only it is affecting my daughter but my son my partner, to be honest the entire family. It has completely changed me as a person. The itch has affected my entire family. Hoping for better days.
Sophia’s Story with BRIC – a long road to diagnosis
Sophia has been itchy for as long as I can remember…as she was able to scratch better with age, it just got worse. At first, when she was a baby, her pediatrician thought it was eczema and gave me hydrocortisone. As the itching got worse, we thought it best to go the a dermatologist. He too diagnosed her with eczema. She would tell me that the inside of her ears itched and I knew it was internal. She would wake up at all hours screaming and inconsolable. We would wrap her in ice packs or give her cool baths. I asked to see an allergist…had her tested for food allergies at the age of 3.
Everything came back negative for allergies but by the grace of God they had accidentally tested her liver enzymes. They were astronomical. They were supposed to be around 300 and hers were 2500. Her pediatrician sent her to a gastroenterologist at Akron Childrens. He was convinced her numbers were high due to bone growth and dismissed it.
In the meantime, her baby teeth are coming in with cavities (she was deficient in vitamin d due to bric). By age 4, she had around 15 cavities. Her pediatrician, dermatologist, and allergist were all communicating trying to find out what this could be. In the meantime, I took her to a psychologist thinking maybe it was anxiety. More blood work…tested positive for scleroderma…sent to rheumatologist. Ended up being a false positive. That doctor did a biopsy for mastitis…came back negative. At this time, she was so bad that she couldn’t wear underwear or socks because they would snag on all her wounds or it would rub her raw. She was on a total of 5 different antihistamines and also steroids. She was 5 years old by this time and I was pregnant and exhausted. Finally, I reached out to Cleveland Clinic. Started out with a dermatologist who put her on a 6th antihistamine. After 2 days I took her off all meds and we did more blood work. Her ANA came back positive so again we were directed to a rheumatologist. He was at a loss, but because of her elevated liver levels he directed us back to Clevelands gastroenterologist. She sent away genetic testing.
Finally weeks later we had an answer! BRIC 2. They prescribed her rifampin and Cholestyramine. My mom was talking to drs at UPMC in Pa. They were suggesting solutions that Cleveland hadn’t even heard of. And if she ever needed any kind of liver surgical procedure they would send her to Pittsburgh so we went there to check it out. Loved the Dr there.. he takes his time and tries his best to answer any questions we have.. pretty sure he’s part of these studies..Dr James Squires. They also have us in a test study to find out as much as they can about her and this disorder.
Currently she is on Welchol (in place of Cholestyramine because she can now swallow pills). She takes Ursodiol twice a day and naltrexone once a day unless she has a flair..then she takes it twice a day. Her last flair was about a year and a half ago…the longest she’s ever gone. They monitor her liver with ultrasounds and blood work once a year unless she has an episode. Can’t tell of any triggers. Sometimes she has anxiety in certain situations and she scratches automatically. She’s very sensitive to clothes, socks, shoes etc…
My beautiful little girl Yolanda has a very rare liver condition called Benign Recurrent Intrahepatic Cholestasis (BRIC) which is a version of condition called Progressive Familial Intrahepatic Cholestasis (PFIC). The difference between BRIC and PFIC is that BRIC comes and goes and PFIC often progresses quickly with time.
Yolanda has now been mostly symptom free for three years. However from birth until around 7 months old, life was very difficult for her. She was constantly itchy and very unsettled. The itch got worse to the point that it was unbearable. She could not sleep, could barely eat and was in constant pain. It was awful to see our baby in such extreme discomfort. At first we thought it may be an allergy but once that was ruled out, at five months old, liver function tests were done. All came back clear! However, one blood test for ‘Bile Salts’ took a few extra days to come back and the news was not good. Yolanda’s bile salts were more than 200 times the normal level!! This was a clear marker of liver disease, most likely PFIC. Yolanda was admitted to The Children’s Hospital at Westmead Sydney for more tests including a liver biopsy. All tests were inconclusive for a diagnosis but by this time her bile salts were 500 times the normal level and she was in extreme pain from the horrendous itch.
Being so rare, there was very little information available about PFIC, resources were limited and it was a confusing time. While it looked to be PFIC, we had to wait months for genetic testing – which finally confirmed she has PFIC 2. ( with a presentation of BRIC 2). Three years ago there were no drugs that treat PFIC/BRIC. However there were a few drugs that can sometimes help stop the itch. She was put on Urso for a few weeks with no luck, however, an alternative- Rifampicin was tried and the itch decreased to a point where Yolanda could function without pain. After some months we stopped the medication and she remained itch free. While Rifampcin can help PFIC it is not an ideal drug as it it processed though the liver. We are still unsure if the medication stopped the attack or it was an episode of BRIC that ended on its own The itch still comes and goes but it’s nothing like those awful, horrible months where she was unbearable itchy.
The symptoms could come back at any time. This keeps me focused on researching treatments and raising awareness of PFIC. In last three years I have advocated passionately for two trial drugs that can directly help our PFIC children and even stop the need for surgery and transplant in some cases. Seeing my little baby is so much pain and knowing it could come back at any time has kept me driven to find safe and effective treatment for PFIC. Our Children deserve freedom form these awful symptoms.
Armando was diagnosed with PFIC when he was 5 months old. He was born a seemingly healthy baby but around 3 months old he started to cry frequently and was inconsolable a lot of the time. Shortly after that he started to become itchy. At first we thought he had allergies so we tried different soaps and laundry detergents and it made no difference.
Over the next couple months he became so itchy that his sheets would be stained with blood when he woke up. It was at this point that we also noticed he started to look yellow. I knew that wasn’t normal for a baby his age so I took him in to the doctor that day. The doctor ordered some blood tests and sent us home. When the results of the blood tests came in our doctor immediately sent Armando to be checked out by a specialist. The specialist admitted Armando to the hospital that same day as he wasn’t sure what was going on and wanted to run multiple tests (x rays, ultrasounds, liver biopsy, genetic test) over what turned out to be a long week in the hospital.
When Armando was released from the hospital we were not given an actual diagnosis, we were just told that in the end his liver won’t do well. About a month later genetic testing confirmed Armando had PFIC 2. This was by far the most difficult time for us. Armando was extremely itchy, losing weight, very irritable and inconsolable, and we had just learned that he would most likely require a liver transplant sometime in his childhood.
He was started on a few different medications and multiple different vitamins. A few weeks after that his doctor wanted to give him an NG tube because he was losing weight and refusing to drink a bottle with a specialized formula. After a call with the doctor and a very long 18 hours without eating anything, Armando finally took the bottle and we were able to avoid the NG tube! Armando has been on multiple different medications which some have worked for a season and then seem to stop helping altogether. Currently, he is about to start on one of the new trial drugs and we are hopeful that this could finally give him some relief from the constant itch! It’s really difficult watching Armando when he is in pain and scratching himself for the majority of the day and we can’t do anything to help him. We are hopeful that there will be effective treatments for PFIC in the future! Armando is such a loving, adventurous, joyful boy and we can’t wait for him to finally be itch free one day!